Correcting Knee Malalignment in Osteoarthritis: Why Mechanical Correction Matters

Correcting Knee Malalignment in Osteoarthritis: Why Mechanical Correction Matters
Knee osteoarthritis is not always a problem of cartilage degeneration alone. In some patients, the alignment of the lower limb plays a major role in determining how force passes through the knee and which compartment experiences the greatest stress.
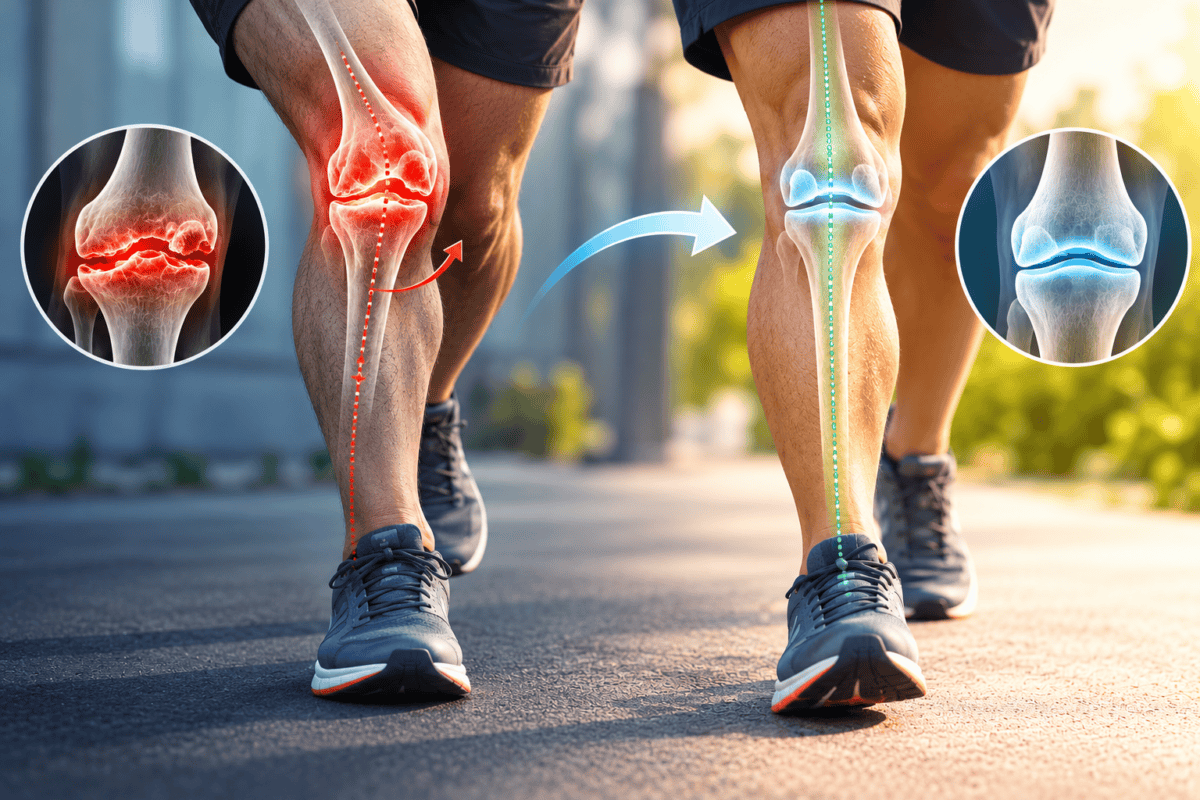
Consider a patient who experiences pain on the inner side of the knee while walking, climbing stairs or standing for prolonged periods. If examination and weight-bearing X-rays reveal varus alignment with medial-compartment degeneration, the problem may involve both joint damage and abnormal mechanical loading. Treating symptoms without assessing this mechanical factor can leave an important part of the condition unaddressed.
At N K Aggarwal Joints & Spine Centre, Ludhiana, assessment and correction of malalignment are important considerations in knee-preservation treatment. The objective is to identify excessive compartmental loading and determine whether it can be reduced through conservative measures or a corrective procedure.
How Malalignment Changes Knee Loading
The mechanical axis of the lower limb describes the relationship between the centres of the hip, knee and ankle. Its position helps explain how body weight is transmitted through the knee during standing and movement.
In varus alignment, commonly described as bow-legged, loading tends to shift towards the medial compartment. In valgus alignment, commonly described as knock-kneed, loading may increase on the lateral compartment. A prospective study published in JAMA by Sharma and colleagues found that varus alignment was associated with approximately four times the adjusted odds of medial-compartment osteoarthritis progression. Valgus alignment was associated with nearly five times the adjusted odds of lateral-compartment progression over 18 months.[1]
When Conservative Measures Can Help
Not every alignment abnormality requires surgery. The first consideration is whether the loading pattern can be managed with non-operative treatment and whether the deformity is flexible or fixed.
A compartment-specific unloader brace can apply a corrective force intended to reduce loading on the affected side. Strengthening, gait training and appropriate activity modification can improve function and help manage symptoms. Treatment depends on the degree of deformity, symptoms, stability, functional requirements and response to previous management.
High Tibial Osteotomy: Correcting the Mechanical Axis
High tibial osteotomy (HTO) is an established joint-preserving procedure for selected patients with malalignment and compartment-specific osteoarthritis. It is particularly relevant for varus alignment with predominantly medial-compartment disease. A systematic review by He and colleagues examined HTO for knee osteoarthritis and reported improvements in clinical outcomes across the included literature, while noting differences between techniques and limitations in the evidence.[3] The American Academy of Orthopaedic Surgeons states that HTO may be considered to improve pain and function in appropriately selected patients with unicompartmental knee osteoarthritis.[4]
HTO is not suitable for everyone. Cartilage damage, deformity location, ligament stability, activity demands and the condition of the remaining joint all influence whether the procedure is appropriate.
Malalignment Affecting the Outer Side of the Knee
Valgus deformity with lateral-compartment osteoarthritis requires a different assessment from the more commonly discussed varus knee. A systematic review by Coakley and colleagues examined HTO outcomes for valgus knees, including 517 knees across 17 studies. The review found evidence of clinical benefit, but also highlighted limitations in the available evidence and uncertainty regarding quality-of-life outcomes.[5]
The important principle is that alignment correction must match the affected compartment and the anatomical source of the deformity. A procedure designed for one alignment pattern should not automatically be applied to another.
Alignment Correction Within the Ludhiana Protocol
The Ludhiana Protocol considers the mechanical condition of the knee alongside its biological and structural status. The aim is to determine whether abnormal loading is contributing to symptoms and whether that factor can be addressed. Depending on the clinical findings, treatment may include rehabilitation, unloading measures or a selected corrective procedure. PRP or Autologous Growth Factor Concentrate and High Molecular Weight Hyaluronic Acid, along with systemic treatment is also advised for their respective roles in knee-preservation treatment. These approaches serve different purposes. Biological injections do not substitute for correcting a deformity, just as a corrective procedure does not remove the need to assess the remaining joint and its biological condition.
In selected cases, soft-tissue balancing techniques, including ligament pie-crusting, (Needle Plasty) is done to correct mild to moderate varus deformity. These techniques must be distinguished from osteotomy: they are not interchangeable, and their suitability depends on the deformity, knee stability and correction required.
The central principle is to identify the dominant problem in each knee and match the treatment to it. Alignment correction is important when abnormal mechanical loading is clinically meaningful, but it is not a universal requirement for every patient with osteoarthritis.
Who Should Be Evaluated for Malalignment?
A detailed alignment assessment deserves particular attention when a patient has:
- Pain concentrated predominantly on the inner or outer side of the knee.
- Bow-legged or knock-kneed alignment with persistent symptoms.
- Compartment-specific joint-space narrowing on weight-bearing X-rays.
- Ongoing functional limitation despite appropriate conservative treatment.
- A potential indication for a joint-preserving corrective procedure.
Patients with early or moderate compartmental disease may have different preservation options from those with severe bone-on-bone arthritis, extensive structural damage or major fixed deformity. Decisions should be based on the complete clinical and radiographic picture, not a single X-ray finding.
Clinical Conclusion
Malalignment can influence how force is distributed across the knee and contribute to compartment-specific osteoarthritis progression. Identifying it allows clinicians to address a mechanical factor that symptom-relieving treatment alone may not correct.
At N K Aggarwal Joints & Spine Centre, Ludhiana, alignment assessment is an important consideration in selected knee-preservation cases. Evaluation of the mechanical axis, source of deformity and condition of the affected compartment helps determine whether conservative unloading or a corrective procedure is justified.
The goal is not simply to make the leg appear straighter. It is to improve knee mechanics in a way that suits the patient’s anatomy, disease severity and functional needs.
Medical References
[1] Sharma L, Song J, Felson DT, et al. The role of knee alignment in disease progression and functional decline in knee osteoarthritis. JAMA. 2001;286(2):188–195.
[2] Harvey J, Eltayeb M, Moulder EH, et al. Compensatory mechanisms for proximal and distal joint alignment and gait in varus knee osteoarthritis treated with high tibial osteotomy: a systematic review. Journal of Orthopaedics. 2024;54:148–157.
[3] He M, Zhong X, Li Z, Shen K, Zeng W. Progress in the treatment of knee osteoarthritis with high tibial osteotomy: a systematic review. Systematic Reviews. 2021;10:56.
[4] American Academy of Orthopaedic Surgeons. Management of Osteoarthritis of the Knee (Non-Arthroplasty): Evidence-Based Clinical Practice Guideline. 2021.
[5] Coakley A, McNicholas M, Biant L, Tawy G. A systematic review of outcomes of high tibial osteotomy for the valgus knee. The Knee. 2023;40:97–110.
[6] Systematic review examining the relationship between coronal plane alignment and patient-reported outcomes following high tibial osteotomy.
[7] Xie T, Brouwer RW, van den Akker-Scheek I, et al. Clinical relevance of joint line obliquity after high tibial osteotomy for medial knee osteoarthritis remains controversial: a systematic review. Knee Surgery, Sports Traumatology, Arthroscopy. 2023;31:4355–4367.